We talk a lot about the efforts within our profession at increasing diversity, inclusion and equity, but this study grants a unique perspective on that by surveying our patients on their experience of DEI in the ED.
The authors surveyed about 1700 patients, with 800 responding, at a large ED in Detroit. The population was majority black, and had a wide degree of variability in socioeconomic status.
Overall the patients felt that the staff had no biased or prejudiced interactions with people of different races. However, they felt that people from lower socioeconomic levels, transgender patients, and those that had mental health issues were treated unfairly. They also noted (about17% of respondents) harassment of ED staff by another patient.
You may have seen the headline.
93 million CT examinations conducted on 62 million US patients in 2023 projected to lead to 103000 new cancer diagnoses accounting for 5% of new cancers.
The details of the modeling can be found here, https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2832778.
What does this have to do with administration?
The solutions rely on administrative involvement:
There’s an editorial here, https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2832782 and a commentary with interviews that put the findings nicely in context here https://arstechnica.com/health/2025/04/ct-scans-could-cause-5-of-cancers-study-finds-experts-note-uncertainty/ (including pointing out that lifetime risk of cancer in the US is 40% and the increase from CT scanning on the order of 0.1% / scan).
This study was the first look at the author's experiences with racial disparities in head and neck trauma in children. It looked at community EDs, and found that white children were more likely to be diagnosed with concussion compared to black children. White children were more likely to be seen as a result of sports or motor vehicle accidents, while black children were more likely to be seen as a result of an assault.
This study revealed the need for further research into the cause of the disparities in care that they identified.
A recent cohort study performed by the NCAA and US Department of Defense looked at NCAA athletes and military cadets who had suffered a concussion.
The study included 1661 NCAA athletes and military cadets, mean age was about 18 years, and 45% were women.
In these groupings, 813 people took over-the-counter pain relievers after their concussion and 848 people did not take any pain relievers.
Analgesics used included medications such as acetaminophen or NSAIDs such as ibuprofen.
Acetaminophen (n = 600), NSAIDs (n = 75), and those taking both (n = 78).
1) 50% recovery
Better teamwork creates better outcomes in emergency medicine. This study investigated how communication practices between physicians and nurses in the ED influence team dynamics and the sense of belonging to the healthcare team.
Methods: 38 emergency physicians and emergency nurses from EDs within a single metropolitan area participated in focus groups.
Positive Influences on Team Belonging:
Negative Influences on Team Belonging:
The findings emphasize the importance of fostering positive communication practices to enhance team dynamics, cohesiveness, and overall well-being within ED healthcare teams.
Ramadan is the holy month in the Islam faith, where observers will fast from sunrise to sunset. This includes food, water, some medications, smoking and sex. This can obviously have some impact on patients' health, especially when presenting to the ED. Here are some considerations to keep in mind:
As with everything, maintaining cultural awareness and compassion will help to
Nurse Practitioners and Physician Assistants practice alongside Physicians in Emergency Departments. In 2021, an estimated 17,679 NPs and PAs worked in EDs.
How long do NPs and PAs continue in Emergency Medicine practice?
An analysis of Medicare data reports that over the eight years of the study, the annual attrition rate averaged 13.8%, or almost 1 in 7 leaving Emergency Medicine practice every year. At the time of attrition, the median age for women was 40.2 years (IQR 33.8 to 49.9) and for men was 45.9 (IQR 37.8 to 56.3).
For additional breakdown and discussion of these numbers, see Gettel CJ, Chosh R, Rothenberg, et al. Workforce Attrition Among Emergency Medicine Non-Physician Practitioners. Ann Emerg Med, in press, https://www.annemergmed.com/article/S0196-0644(24)01294-0/fulltext.
On March 18, 2022, Congress passed the Dr. Lorna Breen Health Care Provider Protection Act, named after an emergency medicine physician who died by suicide during the pandemic. This landmark legislation allocated $103 million across 45 organizations to introduce evidence-based measures to mitigate and prevent burnout.
As a result, the Impact Wellbeing Guide was developed, outlining the six key evidence-based action steps for organization leaders to address health care workers’ professional well-being listed below:
The Guide is designed to help hospital leaders and executives accelerate or supplement professional wellbeing work in their hospitals at the operational level.
A PDF of the full guide is available from the CDC: https://www.cdc.gov/niosh/docs/2024-109/
Clinical practice in the world of the Electronic Medical Record has made many a clinician question the value of electronic reminders.
Banners warn of sepsis, the need for repeat evaluation, vital signs outside expected limits, wait times, and risks for readmission.
Can they instead help ED flow?
Sayan Dutta and colleagues suggest that they can. When clinicians chose to receive notice of a lab or imaging result, push notification reduced time between final result and ED disposition by 18 minutes (95% CI: 15-21 minutes).
The likely key here? Clinicians actively chose when and about what to be notified.
See: Result Push Notifications Improve Time to Emergency Department Disposition: A Pragmatic Observational Study, Annals of Emergency Medicine, 85(1), 53-62. https://www.annemergmed.com/article/S0196-0644(24)00404-9/abstract.
From all of us at UMEM, Happy Thanksgiving!!
We are incredibly Thankful for each of you and all that you do to care for patients and their families.
We are Thankful for those legends who have blazed the path in EM like Greg Henry who the EM community lost yesterday. Our thoughts are with his family. Thank you Dr. Henry for inspiring so many of us. Our pearls today are two of his famous quotes:
“Medicine is show business for ugly people.”
“You don’t go to Disney and see Mickey taking a smoke break. You have to be on when you are on shift”
Gooble, gooble,… gulp, some food for thought on the eve of Thanksgiving.
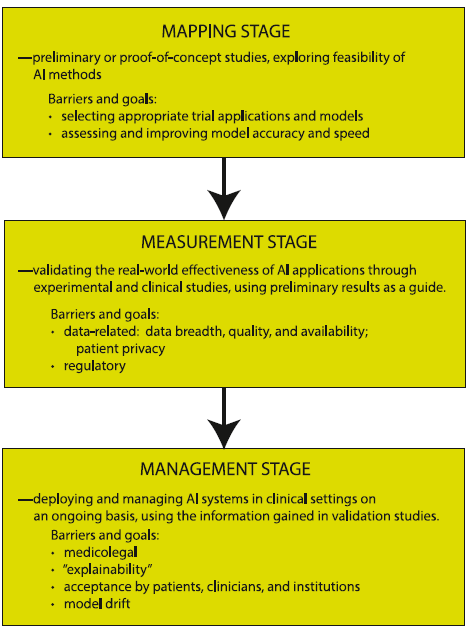
The development of artificial intelligence (AI) in emergency medicine is well under way. The schematic below and accompanying reference presents the anticipated stages in the process of AI development, including important features, considerations, and challenges as we move towards increased integration of AI in our practice of EM.

Does physician altruism influence quality metrics? This study suggests yes.
45 physicians were defined as “altruistic” based on their willingness to share a $250 cash prize with a stranger in an on-line version of the dictator game, something you might have played in an economics class.
Of 250 physicians drawn from primary care and cardiology, 45 met the definition of altruistic and 205 did not.
Overall, patients of altruistic physicians:
The authors suggest that this difference may be on account of altruistic physicians being more willing to consider the appropriateness of tests or treatment or “devote more time and energy to their patients.”
They also note that while most physicians were categorized as not altruistic, at 18% this group of physicians exceeds the 5% of the general US population that would meet this definition.
Perhaps there is something quantitatively demonstrable to being a “good” doctor.
See https://jamanetwork.com/journals/jama-health-forum/fullarticle/2824419

Traditional Medicare now covers < 50% of Medicare beneficiaries. It reimburses on a fee-for-service basis. For beneficiaries, it includes deductibles and coinsurance requirements that yield average annual out-of-pocket expenses measured in the thousands of dollars.
Medicare Advantage, the new alternative, has grown quickly. Plans typically promise beneficiaries fewer co-pays and more services. It relies on private insurers (think United, Blue Cross, Kaiser Permanente) to coordinate care and rein in costs. Subsidies to Medicare Advantage have helped spur growth, subsidies that mean costs per beneficiary for Medicare Advantage exceed those for traditional Medicare.
Which means Medicare still needs to figure out how to save money and remain viable while the US population over 65 grows.
When listening to a lecture about Medicare or reading a study that uses Medicare data, take a moment to ask “Which Medicare? Fee-for-service? Or Advantage?”
For a take on the future of Medicare, see McWilliams JM, The Future of Medicare and the Role of Traditional Medicare as Competitor, NEJM, August 22/29, 763-769.
To understand why Medicare Advantage plans are popular, see https://www.kff.org/medicare/issue-brief/10-reasons-why-medicare-advantage-enrollment-is-growing-and-why-it-matters/.
“I’m not going to the hospital, my father died in a hospital.”
In planning a study it’s a good practice to consider what confounding variables you may need to look out for.
Confounding variables are associated with the predictor (independent) and outcome (dependent) variables, but they are not in the causal chain. In the above example, disease is likely the predictor variable, death is the outcome variable, and going to the hospital is a confounder. Of course, this assumes the death was not iatrogenic; then the hospital would be in the causal chain.
Patients may be selected for interventions based on severity of disease, functional status, education level, and other factors, and these may be confounders.
Confounding can be addressed at the design stage, by:
It can be addressed in the analysis stage by:
This retrospective study found that while overall rates of antibiotic prescriptions for viral URIs were low (that's good!), patients identified as non Hispanic white were prescribed antibiotics, despite guidelines advising against them, at a higher rate than non white patients (that's bad). It also found that in areas of socioeconomic deprivation, the prescribing rates were lower across all races than in more affluent areas (that's good and bad!)
Participation in meetings is an expected part of most (if not all) of our jobs. How many of these meetings are necessary? Could some of the “work” of meetings be accomplished with a few emails or other asynchronous forms of communication? Are meetings cluttering your schedule and making it impossible to get any real work done?
Some answers to these questions are offered in a Harvard Business Review article from March 2022.
Key points include:
Advantages to fewer meetings:
Authors recommend holding meetings only when “absolutely” necessary. That typically includes:
Early administration of antibiotics for open fractures can reduce serious bone and soft tissue infections, with a common goal being antibiotic administration within one hour of injury.
In this study, there were 523 patients treated by EMS who had an open extremity fracture.
The median time from EMS dispatch until antibiotic administration was 31 minutes. 99% of the patients who received antibiotics received them within one hour of EMS dispatch. Prehospital times were on average 10 minutes longer for those patients who received antibiotics. The majority of these patients received cefazolin, followed by ceftriaxone, ampicillin, gentamicin and piperacillin/tazobactam. None of these patients required management for an allergic reaction or anaphylaxis. Five patients (1%) who received prehospital antibiotics and 159 patients who did not (1.4%) had a subsequent infection based on ICD codes.
Bottom line: In this small group, it was safe to administer antibiotics to a patient with an isolated open extremity fracture and the medication was able to be delivered earlier. Larger studies will be needed to see the impact of this practice on the development of osteomyelitis or soft tissue infections.
“Administrative harm” (defined as “the adverse consequences of administrative decisions within health care”) is a relatively new term for challenges that arise in complex health care work environments.
41 mostly hospitalists participating in interviews and focus groups found that the concept resonated, and that administrative harms could arise at all levels of leadership, negatively impacted both workforce and patients, were challenging to measure, and pointed to a lack of leadership responsibility and accountability. The group also suggested many approaches and solutions for prevention.
The article is here, https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2820266. If interested, take a look at the thematic tables 2 and 3.
There is a brief editorial comment here, https://jamanetwork.com/journals/jamainternalmedicine/article-abstract/2820275.
Author:
Gabriella Miller (She/Her)
Clinical Instructor
Department of Emergency Medicine
University of Maryland School of Medicine
Doxycycline PEP for the prevention of bacterial STIs.
The CDC now recommends “doxy PEP” for high-risk individuals. Doxycycline post-exposure prophylaxis (doxy PEP) is a prescription for patients to self-administer 200 mg doxycycline by mouth within 72 hours after anal, oral, or vaginal sex to prevent the transmission of chlamydia, gonorrhea, and syphilis. The CDC defines “high-risk” as men who have sex with men (MSM) and transgender women (TGW) who have been diagnosed with a bacterial STI within the past 12 months. They summarize the findings of the French IPERGAY and ANRS DOXYVAC studies, as well as the US DoxyPEP study, which all show promising reductions in risk ratios or hazard ratios of decreasing bacterial STI transmission on high-risk populations, including those who are taking PrEP for HIV. No significant adverse events related to doxy PEP have been reported.
Conclusion:
Counsel patients at high risk for bacterial STIs regarding the prescription of doxy-PEP for patient self-administration within 72 hours after sex.